


 It’s easy to assume that anyone with an “advanced degree” is exempt from overtime. For physicians managing a practice, that assumption can be costly. The framework for determining which employees are exempt from overtime pay is established by the federal Fair Labor Standards Act (“FLSA”) and the New York Labor Law (“NYLL”).
What Is the FLSA and How Does It Apply to Overtime Pay?
The FLSA is the primary federal law governing minimum wage, overtime pay, recordkeeping, and youth employment standards. Under the FLSA, non-exempt employees must be paid overtime at a rate of no less than one and one-half (1½) times their regular rate for all hours worked over forty (40) in a single workweek. The NYLL has similar overtime provisions and generally follows the FLSA in areas its own provisions do not address.
What Individuals are Exempt from Overtime Pay Under the FLSA and the NYLL?
For an employee to be exempt from overtime wages under both the FLSA and the NYLL, the employee must pass three tests: (1) Salary Basis Test, (2) Job Duties Test, and (3) Salary Level Test.
The Salary Basis Test.
Under both the FLSA and NYLL, an exempt employee generally must be salaried and paid a predetermined, fixed salary. However, the FLSA provides that licensed physicians engaged in the practice of medicine need not meet any of the three tests. “Physician” here includes podiatrists, dentists, veterinarians, and optometrists. This carve-out also applies to physician residents and interns holding a requisite academic degree (e.g., M.D., D.O., D.P.M.) but does not extend to pharmacists, PAs, NPs, RNs, or similar roles. Most PAs, pharmacists, and certain practice staff, such as practice managers, are salaried employees and therefore may be exempt if they meet the following two tests.
The Job Duties Test.
Employees properly classified as professional, administrative, or executive employees under both the NYLL and FLSA pass the Job Duties Test. These are not formal labels preassigned by a government agency; rather, an employer determines the classification by reviewing the employee’s actual job duties. The classification is based on general work duties, not job title alone, and is usually scrutinized only if an employee disputes their overtime status. Executive employees carry out managerial duties such as managing the practice or office, regularly directing two or more employees, and having sufficient authority and discretion to hire, fire, or make other employment-status decisions. Practice managers generally qualify because they oversee office operations, supervise staff, and hold hiring/firing authority.
Administrative employees’ primary duties involve performing office or nonmanual field work directly related to management or general operations, regularly assisting an employer or executive employee, and exercising significant discretionary powers in performing their duties. Compliance officers and human resources personnel generally qualify because they perform office work, assist their employer, and exercise discretion.
Professional employees must meet three criteria to pass the Job Duties Test: (1) their primary duty requires advanced knowledge in a field of science or learning customarily acquired through prolonged specialized intellectual instruction and study, (2) their work requires regular exercise of discretion, and (3) their work is predominantly intellectual and varied in character such that output cannot be standardized in relation to a given time period.
Whether an employee qualifies as a “professional employee” is determined on a case-by-case basis, and no job title alone guarantees the classification. The analysis focuses on whether the job’s primary duty requires specialized academic instruction and uses advanced knowledge typically acquired through prolonged study. “Advanced knowledge” means the employee exercises discretion and judgment characteristic of the profession at issue. Although the required advanced knowledge need not come from a specialized advanced degree, an employer’s minimum academic qualifications and whether most employees in that role hold such a degree are considered. Work is “predominantly intellectual and varied” when it is not routine mental, manual, mechanical, or physical work.
Pharmacists, PAs, and RNs (not LPNs) are generally considered professional employees because of their advanced knowledge, routine exercise of discretion, and intellectual work.
The Salary Level Test.
The salary thresholds for the Salary Level Test differ under the FLSA and the NYLL. Employees working in New York must meet the NYLL salary level, while employees in other states must meet the FLSA salary level unless their state imposes its own test for overtime exemption. Under the NYLL, the Salary Level Test applies only to executive and administrative employees. New York defers to the FLSA salary level for professional exempt employees. As of this article’s publication date, for employees outside New York City and Nassau, Suffolk, and Westchester counties, the test is met at a minimum salary of $1,199.10 per week ($1,275.00 per week for New York City, Nassau, Suffolk, and Westchester County employees).
Under the FLSA, the Salary Level Test is met when an employee earns more than $684 per week, regardless of employee type. This means that New York salaried professional employees who satisfy the professional duties test and earn above $684 per week generally meet the salarylevel requirement for overtime exemption.
If My Employee Meets the Criteria, Are They Exempt from Overtime Pay?
If an employee passes all three tests, they are overtime-exempt and are not required by law to be paid overtime for working over 40 hours in a workweek (although an employer can still voluntarily agree to pay overtime). If an employee fails even one test, they must be paid overtime. Failure to pay an eligible employee overtime could require the employer to provide back pay for owed overtime wages. For this reason, it is imperative that practice owners and managers understand these rules to ensure employees are properly compensated and the practice avoids liability for unpaid wages.
Practice owners with questions about the topics outlined in this article can contact Lippes Mathias LLP health care team members Jennifer E. Forward (jforward@lippes.com) or Marc S. Beckman (mbeckman@lippes.com).
 Although the practice is new, the providers each bring over ten years of experience gained by
 As the single orthopedic and spine practice integrated within the hospital system, St. Joseph’s Health Orthopedic and Spine Care can quickly connect with many specialized health care providers, offering the “best of both worlds” from inpatient and outpatient care, as Dr. Raphael explained.
 Dr. Raphael, who was born and raised in Syracuse, followed in the footsteps of his father, Dr.
 led by Dr. Iorio, who specializes in cervical, thoracic and
 The EOS is a prime example of how the St. Joseph’s Health Orthopedics and Spine Care team is utilizing the latest technology available to provide patient-centered care. Rather than stitching together separate x-ray images to get a full-picture view of patients’ needs, as was done previously, the EOS system provides 2D and 3D images of the full skeletal system, helping better inform surgeons in the planning and diagnosis process. St. Joseph’s Health Orthopedics and Spine Care is currently the only practice between Rochester and New York City to utilize this technology.
 Perhaps the most well-known cutting-edge technology utilized by the new practice is one surgeons at St. Joseph’s Health Hospital have been using for many years: minimally-invasive, robotic-assisted surgery and navigation. Dr. Deshmane explained how robotics help minimize patient dissatisfaction from imprecise placement of joint replacement components, especially for younger, high-demand patients.
 In the realm of sports medicine, an exciting non-surgical treatment option the practice offers is orthobiologics utilizing platelet-rich plasma, or PRP. Dr. Raphael described the treatment as a straightforward, in-office procedure that isolates platelets, or growth factors, from the patient’s blood, and then injects them in the needed areas, healing the body with its own tissue rather than a foreign substance that may cause additional tissue deterioration. He said it’s especially useful for treating early arthritis, helping to regrow deteriorated cartilage in a less invasive way. Orthobiologics is one way the team is working on injury prevention and surgery avoidance in sports medicine, Dr. Raphael emphasized.
 An important aspect of the new practice that greatly enhances patient experience is improved access for both patients and referring providers alike, made possible by the group’s integration within the St. Joseph’s Health network. Rather than communicating via text messages or phone calls as they did before, St. Joseph’s Health practitioners now use Epic, one of the biggest medical record systems in the world, to send messages instantly to each other directly within patients’ charts. This improvement in communication
 Reflecting on the success of the practice so far and looking ahead to what’s next, the surgeons at St. Joseph’s Health Orthopedics and Spine Care are excited to build on the team’s progress and momentum.
 the highest level of care to patients, however, as Dr. Deshmane emphasized. “Looking at it from a patient’s perspective, they just want to know that they have options,” he said. “Our practice comes up as a very valid option in our community, with a lot of experience under our belt.”

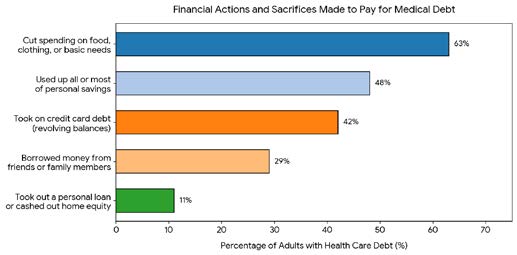 Interesting conversation with a patient last week about their mounting health care debt. Higher premiums, higher deductibles, higher co-pays, more out of formulary uncovered meds all adding up to $45,000 in annual out of pocket costs.

 Disputes in the health care sector are inevitable. Whether they arise between physicians in a group practice, between an ambulatory surgical center and its member surgeons, or between a hospital system and an affiliated provider, conflicts over governance, compensation, non-compete agreements, or operational decisions can quickly consume the time, energy, and resources of all involved. Litigation has long been the default mechanism for resolving such conflicts, but it is rarely the best one. Mediation particularly when guided by an experienced health care attorney serving as mediator offers a faster, more cost effective, and more relationship-preserving alternative that deserves serious consideration.


 Berlucchi had previously worked for Lancaster General Hospital in Lancaster, Pennsylvania and had come to understand how important OBGYN care is for women in rural and underserved populations. “I know what it’s like to be geographically separated from a maternity center,” he explained. Berlucchi partnered with Crouse Hospital to maintain obstetrical services at Auburn Community Hospital.
 ACH as Chief of Obstetrics and Gynecology. A primary reason she decided to join ACH is the small-town community feeling where she can grow meaningful relationships with patients.
 Dr. Bonilla-Martir explained that she also felt drawn to ACH because the obstetrics and gynecology programs are integrated, and that while some complicated cases may need to be referred out to providers in Rochester or Syracuse, they are able to take on many high-risk patients as well as normal pregnancies.
 “Many patients love Dr. Balaya,” said Dr. Bonilla Martir. “As of the beginning of April, he has become a full time physician with us and will be helping us continue to deliver the high-quality care that women in the community need.”
 Another stand-out aspect of the team of OBGYN providers at ACH is the personalized care provided by the staff of midwives. Jennifer MacBlane, CNM, had been coming to ACH on and off for several years before joining the team full time in August of 2025. She echoed the sentiments of her colleagues when it comes to the small community feel of ACH and of the wider Auburn community.
 “The word ‘midwife’ means ‘with woman.’ The whole idea is that we’re with them to help them and develop whatever they need,” MacBlane said. “It’s all-encompassing. Midwives kind of look at the big picture, so we include everybody – your family, your social history, your medical history. We put it all together. It’s a really nice, unique experience because you get a little bit of the warm and fuzzy, but we also do the medical side. We can get you medicine, lab work, testing, we can get you an epidural – we’re qualified to do that. We just look at it a little differently, and we work a little closer with the patient while they’re in labor.”
 “We work together as a group,” shared MacBlane. “Midwives are independent in New York State, but we work together with the physicians to kind of cover our patients and determine the plan for their care collaboratively, which is really nice.”
 recent years and now includes a dedicated women’s imaging center within the hospital. Jubin Jacob, MD, Chair of Radiology at ACH, highlighted advancements in mammography technology offered to women at ACH, including stereotactic biopsies utilizing mammographic guidance and ultrasound equipment that provides 3D images while keeping radiation doses as low as possible. He emphasized how all the technological advancements offered to women at ACH are aimed at enhancing patient experience.
 With the opening of the new Interventional Radiology suite and the recent addition of a physician assistant who will primarily work on further expansion of radiology services, Dr. Jacob said several other advanced treatments and procedures are being offered to women at ACH. Examples of these new offerings are minimally invasive procedures to treat symptomatic fibroids, adenomyosis, and pelvic venous insufficiency, as well as curative ablation treatments for breast cancer tumors in patients who are not surgical candidates. In addition, the team has access to the best quality PET scanner in the region.
 With anticipated changes to the demographics of people in areas surrounding ACH – including a population that’s both aging and also growing due to developments like Micron – Berlucchi is passionate about continuing to expand the OBGYN practice at the health center. Currently in the process of obtaining a grant with the Department of Health, Berlucchi is leading the team toward a vision of comprehensive healthcare for women of all ages including OBGYN and beyond.

 I am an avid reader, belong to two book clubs, and receive a steady stream of great recommendations from my health news feed. Recently, I had the opportunity to read two excellent books by local physician authors: Dr. Mary Jumbelic, retired Chief Medical Examiner of Onondaga County, and Dr. Sarah Matt, surgeon and health technology expert. Two very different books, but both outstanding and musts for your reading list.
 I asked Dr. Jumbelic when she first realized she wanted to write. Throughout her career, she kept journals and notes about her work, not realizing how important they would be later in life. After retiring, she entered a writing contest and then began taking classes, evolving into a seasoned author with an incredible voice that merges technical forensic expertise with deeply personal reflection.
 Dr. Sarah Matt has also drawn on her surgical and technical expertise to write a strategic and highly readable look at the future of technology in health care. A mid-career physician, she has broadened her impact by working across the health technology landscape, including leadership roles with health technology companies and digital health initiatives.


 To safeguard patient care from corporate interference in clinical decisionmaking, New York maintains one of the strictest corporate practice of medicine (“CPOM”) prohibitions in the United States. Under New York law, medical services may be provided only by licensed medical professionals, by professional entities that are owned and controlled exclusively by licensed medical professionals, or by hospitals and other entities expressly authorized under the Public Health Law.

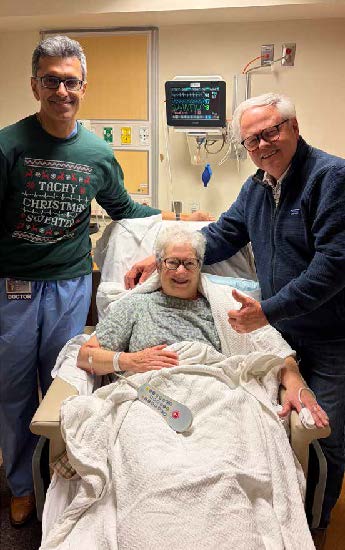 The arrival of Dr. Jorge Romero as Section Chief of Cardiac Electrophysiology and Director of Cardiovascular Research and Innovation is a prime example of increased convenience and accessibility for patients, bringing cutting edge treatments directly into their community. Dr. Taub noted that she initially connected with Dr. Romero to refer a patient for a procedure that couldn’t be done locally.
 “Instead of heating or freezing the tissue, we are creating small holes in the cell membrane, called electroporation. The beauty of this technology is that the cardiac muscle is uniquely sensitive. We only need a small dose of energy to eliminate the triggers for atrial fibrillation located in the pulmonary veins of the patient,” Dr. Romero said, which avoids damage to the smooth muscle of the esophagus, phrenic nerves, and other adjacent structures. This has eliminated the risk of atrial esophageal fistula, a deadly complication that used to happen in 0.2% of ablation cases, but which hasn’t occurred in the 800,000 cases of PFA that have been performed so far worldwide. This new, safer technology greatly benefits the older population, mostly over the ages of 70, who are most likely to suffer from atrial fibrillation, offering improved quality of life and reducing longterm risks. Dr. Romero successfully performed Upstate’s first ablation using the Affera Mapping and Ablation System with the Sphere-9 catheter, a multi-purpose catheter not found at any other facility in New York State outside New York city and Long Island.
 “It’s less morbid; recovery is fast, and outcomes are very similar to open-heart surgery,” said Dr. Kalra. “Transcatheter techniques for the aortic valve are becoming the procedure of choice. Even patients who are at low risk for complications following open heart surgery are eligible for and favor the transcatheter heart valve due to significantly less morbidity following the procedure, and faster return to normal life.”
 Foundational to cardiovascular care is cardiovascular imaging, which is used not only for visualizing and diagnosing cardiac disease, but also during interventional procedures. Under the guidance of Dr. Adeeb Al-Quthami, Director of Cardiovascular Imaging, significant investments in the latest technology have been secured for the benefit of Upstate’s patients.
 “We can visualize the heart to a very high degree in terms of tiny detail,” he said. “If you try to take a picture of something that’s moving, it’s going to blur, especially if what you’re trying to take a picture of is small. With the advancements in technology, we can take a picture of the heart within a fraction of a heartbeat,” identifying patients’ unique anatomy and offering precise, personalized treatment for each patient.
 Launched within the last year, AI assisted plaque analysis software, called HeartFlow, is now helping the Upstate cardiovascular team to better assess a patient’s risk for a future heart attack. Dr. Al-Quthami explained how this new technology offers improvement over the traditional coronary calcium scan.
 By recruiting more cardiovascular experts to Upstate and continuing to invest in the innovative technologies they use, Dr. Tucker highlighted how the Upstate cardiovascular program is committed to staying at the forefront of cardiovascular care.

 When Melanie McNally, MD first began practicing urology, she didn’t anticipate developing a focus on urologic issues specific to women. However, about five years into her practice, she found many women were experiencing urologic health concerns that gynecology was illequipped to manage.